Eye melanoma, medically termed ocular or uveal melanoma, is the most prevalent primary intraocular cancer in adults. While intraocular tumors are relatively uncommon compared to other cancers, they demand early clinical intervention because they develop in delicate, vascular tissues responsible for vision.
Understanding how eye melanoma forms, identifying early warning indicators, and exploring modern treatment modalities are essential steps toward saving sight and preventing systemic spread.
What Is Eye Melanoma?
Melanoma develops in melanocytes the pigment-producing cells that give skin, hair, and eyes their color. Inside the eye, these cells are heavily concentrated in the uvea (the middle vascular layer of the eyeball).
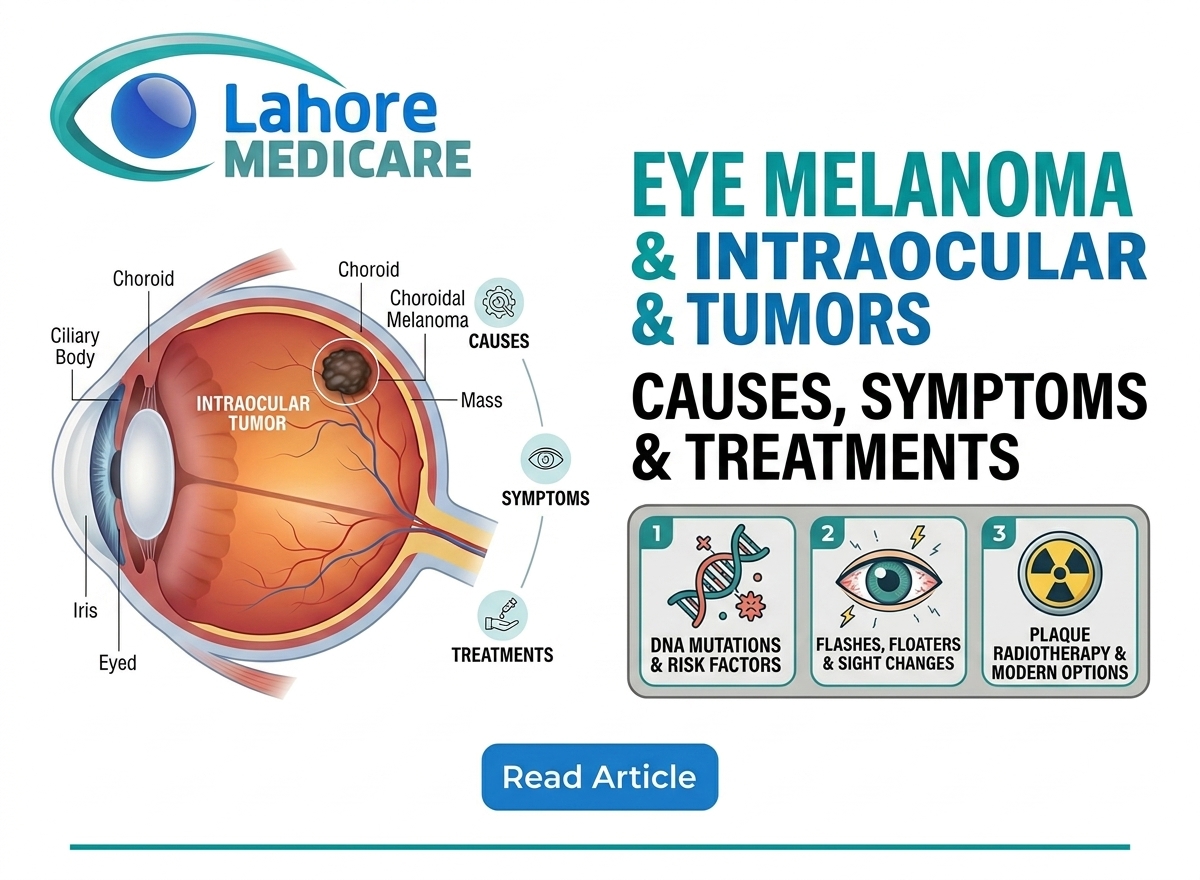
Uveal melanoma accounts for roughly 85–90% of all ocular melanoma cases and is categorized into three specific locations based on where the tumor originates:
- Choroidal Melanoma: Develops in the choroid the dense vascular layer beneath the retina that supplies oxygen and nutrients. This is the most common site for intraocular melanoma.
- Ciliary Body Melanoma: Forms in the muscle tissue behind the iris that controls lens focus and fluid production. These tumors are often hidden from direct view until they grow larger.
- Iris Melanoma: Develops on the colored part of the eye. Because iris tumors are visible on the surface, they are usually detected at an earlier, smaller stage.
Aside from primary ocular melanoma, secondary (metastatic) intraocular tumors can also develop when primary cancers elsewhere most commonly breast cancer in women and lung cancer in men spread to the eye through the bloodstream.
Key Causes and Risk Factors
Eye melanoma occurs when DNA mutations disrupt the normal life cycle of melanocytes, causing them to multiply rapidly and form malignant masses. While the precise molecular triggers are still being researched, several key factors significantly increase an individual’s risk:
- Fair Complexion and Light Eye Color: Individuals with light-colored skin, light hair, and blue, green, or hazel eyes have a higher incidence of uveal melanoma.
- Atypical Skin Nevi or Iris Freckles: A personal history of dysplastic (abnormal) skin moles or benign pigmented spots (nevi) on the iris or choroid increases susceptibility.
- Ocular Melanocytosis: A rare congenital condition characterized by increased pigmentation in the eye tissues and surrounding skin.
- Ultraviolet (UV) Exposure: Excessive exposure to natural sunlight or artificial tanning rays may contribute to conjunctival and iris melanomas.
- Age and Genetic Factors: Risk increases steadily with age, particularly in adults over 50. Certain inherited gene mutations, such as BAP1 tumor suppressor gene alterations, also predispose families to ocular melanoma.
Recognizing Symptoms of Intraocular Tumors
In its earliest stages, eye melanoma often produces no noticeable symptoms and is frequently discovered during routine dilated eye examinations. However, as the intraocular tumor expands and presses against the retina or optic nerve, patients may experience:
- Painless Visual Changes: Blurry vision, loss of peripheral (side) sight, or sudden distortion of straight lines.
- Growing Dark Spot: A dark patch on the iris or white of the eye (sclera) that changes in size or elevation over time.
- Flashes and Floaters: Sudden flashes of light (photopsia) or a sudden increase in floating specks across the visual field caused by retinal traction.
- Altered Pupil Shape: A change in the size, shape, or light reactivity of the pupil.
- Eyeball Displacement: Forward protrusion (proptosis) or altered movement of the eye within the orbit (rare, occurring mostly with large or posterior tumors).
Note: Pain is uncommon in early eye melanoma unless the tumor grows large enough to increase intraocular pressure, causing secondary glaucoma or internal inflammation.
If you observe suspicious dark spots on your iris or sudden visual changes, consulting specialists at an established facility like Lahore Medicare ensures thorough diagnostic evaluation.
How Eye Melanoma Is Diagnosed
To confirm an intraocular tumor and distinguish melanoma from benign nevi, ophthalmologists use specialized imaging tools:
- Dilated Ophthalmoscopy: Detailed examination of the back of the eye using specialized magnifying lenses.
- Ocular Ultrasonography (A-Scan and B-Scan): High-frequency sound waves measure the precise height, thickness, and acoustic density of the internal tumor.
- Optical Coherence Tomography (OCT): Cross-sectional light scans map fluid accumulation, retinal swelling, or structural damage over the tumor site.
- Fundus Fluorescein Angiography (FFA): Special dye injected into the bloodstream highlights abnormal blood vessel growth feeding the intraocular tumor.
Evaluating complex ocular masses alongside common eye diseases and conditions ensures an accurate clinical diagnosis prior to initiating treatment.
Modern Treatment Options for Eye Melanoma
Treatment plans depend on the tumor’s size, location, visual impact, and whether genetic markers indicate a high risk of systemic metastasis. Modern therapies aim to preserve as much vision as possible while eradicating the cancer.
- Plaque Radiotherapy (Brachytherapy): The most common organ-sparing treatment for medium-sized choroidal melanoma. A small customized gold disc carrying radioactive seeds is surgically attached to the outer sclera wall directly over the tumor for several days to destroy malignant cells.
- Proton Beam Therapy: Targeted external beam radiation that delivers precise doses of radiation directly into the eye tumor while sparing surrounding healthy ocular tissue.
- Transpupillary Thermotherapy (TTT) / Laser Therapy: Infrared laser heat used alone for small tumors or in combination with radiation to shrink tumor blood vessels.
- Surgical Resection or Enucleation: Surgical removal of the tumor or complete removal of the eyeball (enucleation) is reserved for large, advanced melanomas where vision cannot be restored or where pain is severe. A realistic prosthetic eye is fitted afterward.
Patients who require diagnostic biopsies, plaque placement, or specialized eye surgeries can access advanced ophthalmic procedures through dedicated tertiary eye centers.
Frequently Asked Questions
Is eye melanoma common?
No. Eye melanoma is relatively rare, accounting for roughly 3–5% of all melanomas worldwide. However, it remains the most common primary intraocular cancer in adults.
Can eye melanoma spread to other parts of the body?
Yes. Uveal melanoma can spread (metastasize) through the bloodstream, most commonly to the liver. Early diagnosis and genetic profiling of the tumor help guide long-term monitoring.
What is the survival rate for eye melanoma?
Prognosis varies significantly depending on tumor size, location, cell type, and genetic markers (such as BAP1 loss). Small, localized intraocular melanomas treated early have high survival rates and excellent local control.
Can sunlight cause eye melanoma?
While UV exposure is strongly linked to skin melanoma and conjunctival tumors, its link to deep choroidal melanoma is less direct. However, wearing UV-blocking sunglasses is strongly recommended for overall eye protection.
How is a benign eye freckle distinguished from eye melanoma?
Eye doctors monitor pigmented spots (nevi) using ocular ultrasound and fundus photography over time. Signs of melanoma include significant thickness, fluid under the retina, orange pigment deposits, and documented growth.
Is surgery always necessary for eye melanoma?
No. Radiation therapies like plaque radiotherapy and proton beam therapy are widely used as alternatives to eye removal, successfully killing tumor cells while conserving the eye structure.
How often should I get my eyes checked if I have a choroidal nevus?
Individuals with a documented choroidal nevus (eye freckle) should undergo a dilated eye exam and ocular imaging every 6 to 12 months to monitor for changes in size or elevation.
What is plaque brachytherapy?
Plaque brachytherapy is a targeted radiation treatment where a small radioactive disc is temporarily attached to the outside wall of the eye directly over the tumor, delivering localized radiation.